Before the Hypothesis
by Serelora
This article was originally published on Medium.
Read full article on MediumDecentralizing Clinical Discovery at the Edge of Care

By Luis Cisneros, CEO of Serelora
Modern medicine has become remarkably good at answering questions.
We have enormous longitudinal datasets, increasingly sophisticated statistical methods, natural-language processing, machine learning, and computing infrastructure capable of analyzing millions of patient records in a fraction of the time such work once required.
Yet there is a more fundamental problem that receives considerably less attention.
Who decides which questions are worth asking?
Most clinical research still begins with some version of the same sequence.
An investigator identifies a question. A hypothesis is formulated. A protocol or analytic design is constructed. Investigators identify the appropriate population or dataset. The data are analyzed. A result is produced.
The machinery has become dramatically faster. The architecture has changed much less.
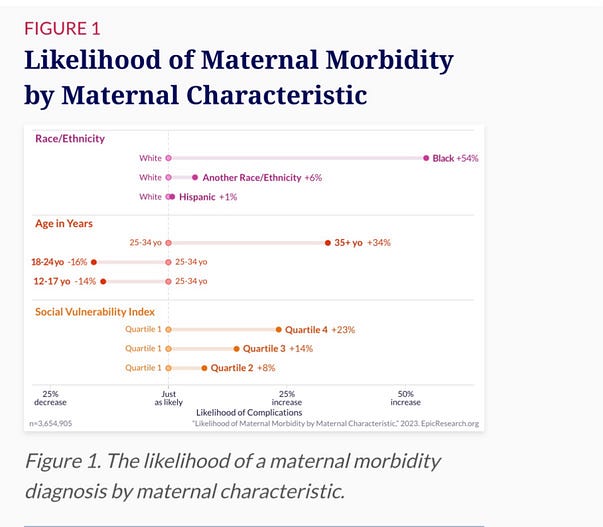
Epic Cosmos provides an unusually clear example. It is an extraordinary accomplishment: longitudinal clinical information from a vast network of healthcare organizations can be interrogated rapidly across very large populations. Epic Research has optimized this further through a process in which an idea is presented, independent clinical and data-science teams investigate the same question, results are reconciled, and findings are disseminated.
That is enormously useful.
But notice where the process begins.
With the idea.
The dataset answers a question that somebody already knew to ask.
There is another model of scientific discovery that healthcare has barely begun to operationalize.
Instead of beginning with the investigator, begin with the patient.
The Missing Step Before the Research Question
Consider how clinical discovery has historically occurred.
A physician repeatedly observes something unexpected.
A treatment behaves differently than anticipated.
A subgroup of patients appears to follow an unusual trajectory.
An adverse effect seems to cluster around a particular phenotype.
Two diseases appear together more often than expected.
A supposedly successful intervention repeatedly fails under circumstances that were never well represented in the original trial.
Perhaps the observation is nothing.
Perhaps it is confounding.
Perhaps it reflects documentation behavior, referral bias, socioeconomic conditions, insurance constraints, adherence, geography, or chance.
But perhaps it is real.
Historically, medicine has depended heavily on the clinician recognizing that something unusual is happening, remembering it, finding colleagues who have seen something similar, and eventually converting the observation into a research question.
That is an extraordinarily inefficient discovery mechanism.
The problem is not that clinicians lack observations.
The problem is that we have never built adequate infrastructure for systematically turning those observations into testable signals.
The alternative research architecture therefore begins differently:
Patients → longitudinal care → emerging pattern → clinical observation → population signal → cross-practice replication → research question → hypothesis → formal study
This is not simply a different way of conducting research.
It changes where research begins.
From Hypothesis-First Research to Signal-First Discovery
Hypothesis-driven research remains indispensable. Once we suspect that an exposure causes an outcome, that one therapy may outperform another, or that a biological mechanism explains a phenotype, rigorous study design is necessary.
But hypothesis-driven research assumes that somebody has already identified the phenomenon worth investigating.
That assumption is rarely discussed.
There is an enormous difference between asking:
“Does X cause Y?”
and asking:
“What is happening here?”
The first question is the beginning of conventional research.
The second is often the beginning of discovery.
A sufficiently sophisticated clinical-data infrastructure should be capable of supporting both.
Most current research systems are optimized for the first.
The opportunity is to build infrastructure for the second.
This could be described as structured serendipity.
Serendipity because the investigator does not specify the finding in advance.
Structured because the process does not end with an anecdote.
A physician observes a possible pattern. The observation is tested against the physician’s population. If a signal remains, it is tested in another population. Then another. Different practices, different demographics, different geographies, different referral patterns, and potentially different data systems become successive opportunities to determine whether the observation survives.
Only then does an interesting pattern become a serious research question.
The sequence becomes:
observe → detect → replicate → explain → test
rather than simply:
hypothesize → query → analyze → publish
The Limits of the Institutional Dataset
The distinction becomes particularly important when discussing enormous datasets such as Epic Cosmos.
The limitation is not size.
The limitation is topology.
Epic contains substantial outpatient data. Cosmos includes primary care, specialists, hospital care, and other longitudinal information from participating organizations.
But outpatient care is not synonymous with outpatient care occurring inside a large integrated health system.
The healthcare experienced by an actual patient is far more fragmented.
A patient may receive hypertension management from an independent internist, hormone treatment from an endocrinologist using another EHR, psychotherapy through a behavioral-health platform, physical therapy from a standalone practice, dental treatment in an electronic dental record, medications through a retail pharmacy, imaging through an independent radiology group, and episodic care through urgent care.
The patient is longitudinal.
The information architecture is not.
This distinction matters because institutional datasets inevitably inherit the boundaries of the institutions and technologies from which they are assembled.
A dataset can contain hundreds of millions of records and still systematically miss portions of the patient’s clinical reality.
That is not a criticism of the dataset. It is a property of its architecture.
The hospital EHR market illustrates the issue particularly well. Large health systems have undergone substantial technological consolidation. The ambulatory market remains considerably more heterogeneous. Move farther from hospital-affiliated medicine into behavioral health, dentistry, rehabilitation, independent specialty practices, and other forms of community care, and fragmentation becomes even more pronounced.
These settings should not be treated merely as missing feeds into a larger centralized database.
They may represent something more valuable.
Independent points of scientific observation.
Research at the Edge of Care
Much of computing has undergone a conceptual transition from centralized processing toward distributed or edge architectures.
Clinical research can undergo a similar transition.
An independent endocrinologist following several thousand patients over many years should not need to belong to a major academic medical center to determine whether an unusual treatment-response pattern exists in that population.
A community obstetrician should not have to wait for an investigator at a university to formulate the question that the obstetrician’s own patients are already raising.
A behavioral-health practice should not merely become another data supplier to an institution capable of performing analysis.
The analytical capability itself can move outward.
That creates a different unit of scientific discovery.
The practice becomes a discovery node.
One practice finding an association is interesting.
Ten independent practices observing the same association under different circumstances is considerably more interesting.
One hundred practices reproducing it across heterogeneous populations may justify an entirely different level of investigation.
Importantly, replication can begin before the traditional formal study rather than occurring only after publication.
This changes the direction of research.
Under the conventional model, the investigator moves outward toward clinical sites after deciding what question must be answered.
Under a distributed model, observations move inward from clinical sites until an emerging pattern becomes important enough to demand investigation.
The research infrastructure is pulled toward the phenomenon rather than the population being pulled toward the investigator.
A Publication Engine Is Not a Discovery Engine
There is a temptation to treat these differences as criticisms of large-scale research platforms. That misses the point.
A publication engine is not inherently a bad thing.
Medicine needs efficient mechanisms for testing existing questions, reproducing previous findings, quantifying associations in larger populations, examining subgroup effects, and determining whether observations established elsewhere remain true in real-world populations.
Platforms such as Cosmos dramatically reduce the cost and time necessary to perform those analyses.
That is valuable.
But optimization has consequences.
If the system begins with a question, then increasing its efficiency primarily allows us to answer more questions more quickly.
It does not necessarily increase the diversity of places from which those questions originate.
This distinction becomes increasingly important in an academic environment in which publication itself carries professional value.
Investigators are rewarded for producing research.
Datasets make research production faster.
Large datasets therefore create an extremely efficient mechanism for converting questions into analyses and analyses into publications.
Again, that is not an insult.
It is an incentive structure.
But an optimized mechanism for answering research questions is not necessarily an optimized mechanism for discovering previously unrecognized clinical phenomena.
The two functions should not be confused.
Democratizing Research Means Democratizing Question Formation
Much of the discussion around democratizing research focuses on access.
Open publications democratize access to knowledge.
Cloud computing democratizes access to computational power.
Large datasets democratize certain forms of analysis.
Decentralized trials can democratize participation.
Artificial intelligence may democratize access to statistical and analytical capabilities.
But the more consequential form of democratization may occur one step earlier.
Who gets to originate the question?
If meaningful population analysis requires employment by a major university, participation in a large health system, privileged access to a proprietary dataset, a research department, biostatistical support, and grant infrastructure, scientific observation remains institutionally concentrated even if the underlying dataset contains millions of patients.
A genuinely distributed discovery architecture would allow physicians and other clinicians at the edge of care to interrogate their own longitudinal populations.
It would allow an independent practice to ask whether what it is seeing is unusual.
It would allow similar practices to determine whether the same pattern exists elsewhere.
And it would allow a research question to emerge from those observations rather than requiring the research question to precede them.
That is a different definition of democratized research.
Not simply allowing more people to conduct studies.
Allowing more people to discover what deserves to be studied.
The Economic Problem Cannot Be Separated From the Scientific One
There is another reason this infrastructure has not emerged organically.
Clinical data has substantial downstream economic value, but the incentives surrounding its generation are poorly aligned.
Physicians, nurses, practices, and patients produce the underlying information through the ordinary process of care.
Other organizations may subsequently normalize it, aggregate it, analyze it, license access to it, use it to train models, recruit patients, perform research, or generate commercial intelligence.
The people closest to the original clinical observation often participate minimally in that downstream value.
That creates an unusual economy.
The clinical system bears much of the cost of producing high-quality information, while the financial rewards for transforming that information into an asset frequently occur elsewhere.
An alternative model would not require clinicians to “sell patient data.”
That is both conceptually crude and ethically problematic.
The more interesting possibility is to allow clinicians and practices to participate in the economic value created through evidence generation.
If a practice identifies a reproducible clinical signal, helps characterize the relevant phenotype, contributes to a multicenter observational study, participates in prospective validation, becomes an investigative site, receives research funding, or contributes to another properly governed evidence-generating activity, that practice can participate in the value created by the research process.
This changes the incentive around clinical data.
Structured data stops being merely a documentation obligation.
It becomes scientific infrastructure.
Better longitudinal information enables better population analysis.
Better population analysis makes useful signals easier to identify.
Useful signals create research opportunities.
Research opportunities create economic incentives for practices to improve the quality and usability of their data.
The result could become a reinforcing cycle rather than another extraction model.
RELATED ARTICLES
Explore more insights and perspectives from our team.